Key Takeaways
- Self-injury often happens when a person is struggling to cope with intense emotions, trauma, sensory overload, pain or frustration.
- There is no single reason for SIB. The same behaviour may have a completely different cause for two different people.
- Self-injury and self-harm are closely related, but they are not always the same. SIB may happen without physical harm being the person’s intention.
- Patterns can tell us a lot. When does SIB happen? What happened just before? What was different that day? What helped afterwards?
- Good support starts with understanding why it is happening. PBS, trauma-informed care, PROACT-SCIPr-UK® and mental health support focus on the person, their distress and what needs to change.
How much pain can a person be carrying for hurting their own body to feel like the only way to cope with it?
For many people, self-injury can become a way of expressing or responding to distress that feels impossible to communicate in any other way. 1 in 10 adults in England report having self-harmed at some point in their lives. Among young adults aged 16–24, that rises to almost 1 in 4.
Research also estimates that self-injurious behaviour affects:
- 42% of autistic people
- 17.4% of adults with learning disabilities
And among people presenting to hospital following self-harm, 52.5% had a recorded mental health diagnosis.
The reasons behind self-injury can be very different. Emotional distress, trauma, communication difficulties, sensory needs and a person’s environment can all play a part. Understanding what is happening for the person is where the right support begins
What is Self-Injurious Behaviour (SIB)?
Self-injurious behaviour (SIB) is when a person hurts their own body, through actions such as cutting, scratching, hitting or biting themselves, banging their head or pulling their hair.
What we see, however, is the injury. What we cannot immediately see is what the person was experiencing before it happened.
For someone struggling with their mental health, self-injury can become a way of responding to emotional pain, intense anxiety, anger, fear, numbness or feelings that have become too overwhelming to manage. Some people describe it as a release. For others, it can be a way of expressing distress when finding the words feels impossible.
This is why understanding self-injury means looking beyond the physical act. What was the person feeling? What happened beforehand? What need is not being met? What makes the urge stronger, and what helps it pass?
These questions can begin to uncover what is driving the behaviour and, importantly, what kind of support the person may need.
What is the Difference Between Self-Injurious Behaviour and Self-Harm?
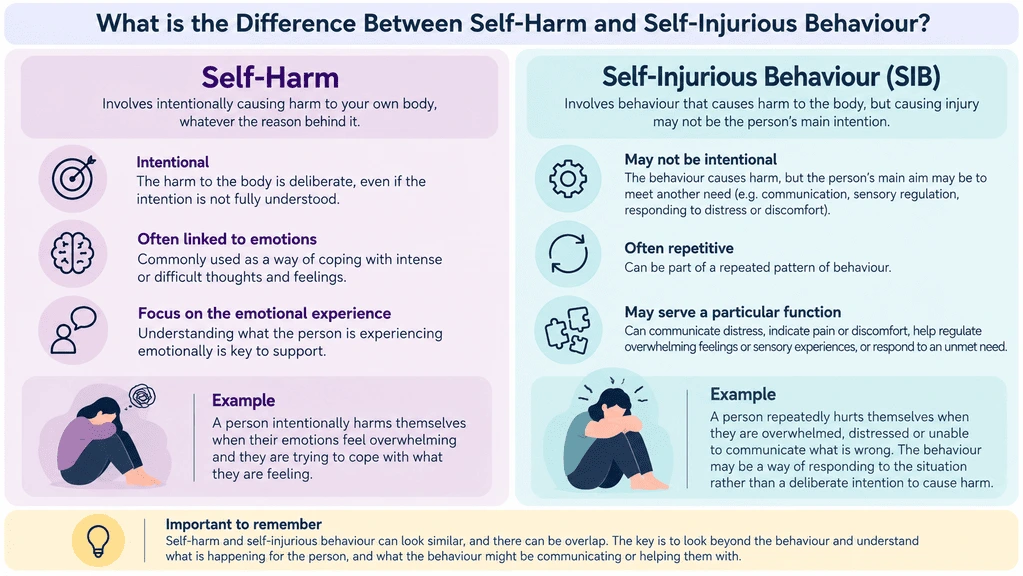
Self-injurious behaviour and self-harm can look similar, but they are not always the same.
Self-harm involves intentionally causing harm to your own body, whatever the reason behind it. Self-injurious behaviour (SIB) is often repetitive and may happen without causing injury being the person’s main aim. Instead, the behaviour may be doing something for the person — communicating distress, responding to pain or discomfort, regulating overwhelming feelings or sensory experiences, or helping them cope with a situation they cannot manage in another way.
Think about a person who is experiencing intense emotional pain and intentionally harms themselves because they feel unable to cope with what they are feeling. This would be described as self-harm. Now think about someone who repeatedly hits themselves when they become extremely distressed or overwhelmed. The behaviour causes physical harm, but causing that harm may not be what the person is trying to achieve. This is more likely to be understood as self-injurious behaviour.
The important question is not simply “Did the person hurt themselves?” but “What was happening for them, and what function did the behaviour serve?”
Types of Self-Injurious Behaviour
Self-injurious behaviours can take many forms, often varying based on individual circumstances. Common types include:
- Head Injuries: Repeatedly hitting the head against hard surfaces, which may indicate frustration or sensory-seeking behaviour.
- Skin Picking or Excessive Scratching: These actions may be tied to anxiety, stress, or sensory processing challenges.
- Self-biting or Hand-biting: Often seen in children or young people with developmental disorders, this behaviour might reflect unmet needs or physical pain.
- Eye Poking or Facial Scratching: Actions that may cause harm to delicate areas, often linked to developmental disabilities.
- Using Sharp Objects to Inflict Harm: A more severe form of self-injury often associated with depression or overwhelming feelings.
Causes and Triggers of Self-Injurious Behaviour
Self-injury can be a sign that something has become too difficult for the person to manage. It might be emotional distress, sensory overload, physical pain, difficulty communicating a need, or something happening in their environment. And what triggers self-injury for one person may have little effect on another.
Emotional Distress and Mental Health
Intense emotions can become difficult to manage, particularly during periods of poor mental health. Anxiety, low mood, fear, frustration, anger or prolonged stress can all contribute to self-injury.
For some people, the behaviour may provide a temporary sense of release or become a way of coping when emotions feel overwhelming and other strategies are difficult to access.
Sensory Overload and Sensory Needs
Noise, bright lights, crowds, touch, strong smells or too much happening at once can become overwhelming. Sensory overload can cause significant distress, particularly for autistic people and others who experience sensory processing differences.
Self-injurious behaviour may occur as the person tries to regulate that experience. The opposite can also happen. When there is too little sensory input, repetitive behaviours may provide stimulation or sensory feedback.
Communication Difficulties and Unmet Needs
Sometimes behaviour communicates something that a person cannot easily say in words.
“I need this to stop.”
“I need a break.”
“Something hurts.”
“I don’t understand what is happening.”
This can be particularly important when someone communicates differently or has difficulty recognising and expressing what they are feeling. Looking at the behaviour as possible communication can help uncover needs that may otherwise be missed.
Pain and Physical Discomfort
A sudden change in behaviour can sometimes be connected to pain, illness or physical discomfort. If a person cannot identify where the pain is coming from or communicate it clearly, self-injury may be one of the ways their distress becomes visible.
This is why physical health should not be overlooked when trying to understand a new or increasing pattern of self-injurious behaviour.
Environment, Relationships and Change
What is happening around the person matters too. Unexpected changes, unfamiliar environments, conflict, demands, disrupted routines, isolation or difficult relationships can increase distress.
Instead of looking only at the person, it can be useful to ask: What has changed around them? What tends to happen immediately before the behaviour? Are there particular places, situations or interactions where it happens more often?
Behaviours of Concern as a Way of Communication
Self-injurious behaviours are often a form of communication, especially for individuals who face challenges expressing their needs, emotions, or pain through traditional means. For children and young people with developmental differences or disabilities, these behaviours might replace verbal communication, acting as a signal for discomfort, distress, or unmet needs.
For example, actions like head banging or hand biting might indicate frustration, physical pain, or an overwhelming sensory environment. When words fail, behaviours of concern become a way to convey messages to caregivers, family members, or professionals.
The link between communication difficulties and self-injurious behaviour highlights the importance of interpreting these actions not just as symptoms of distress but as attempts to interact with the world.
For instance, a child engaging in excessive scratching or skin picking might be expressing anxiety, while a person using sharp objects to harm themselves may be signalling deeper emotional turmoil. These behaviours can also reflect a need for attention, a desire to escape from a stressful situation, or an attempt to manage internal chaos.
Recognising these patterns allows for more compassionate responses, focusing on addressing the underlying communication needs rather than merely stopping the behaviour.

Common Mental Health Challenges Associated with SIB
Self-injurious behaviour can occur alongside a range of mental health challenges, particularly when a person is experiencing intense emotions, persistent distress, traumatic experiences or difficulty regulating how they feel. However, having a mental health diagnosis does not mean someone will experience SIB, and the same behaviour can have very different reasons from one person to another.
Some mental health conditions are more commonly associated with self-injury, including depression, anxiety, borderline personality disorder (BPD) and post-traumatic stress disorder (PTSD). Understanding these connections can give us a clearer picture of what the person may be experiencing and what kind of support could make a difference.
Depression
Depression is one of the most common mental health conditions associated with self-injurious behaviour. People experiencing persistent low mood, feelings of worthlessness, or hopelessness may turn to self-injury as a way to cope with emotional numbness or to feel a sense of control. Acts such as skin picking or using sharp objects can create a temporary distraction from overwhelming sadness or emotional pain. However, this relief is often short-lived, perpetuating a harmful cycle.
Self-injurious behaviour in those with depression often signifies an urgent need for intervention and support. Approaches such as talk therapy, antidepressant medication, or cognitive-behavioural therapy (CBT) can help individuals develop healthier coping mechanisms while addressing the root causes of their depressive symptoms. Encouraging open conversations and providing emotional support can further reduce the stigma and isolation often associated with self-injury.
Anxiety
For people with anxiety, self-injurious behaviour may serve as a maladaptive coping mechanism to manage overwhelming worry or physical symptoms of stress. Behaviours such as hand biting, scratching, or excessive skin picking often emerge as a response to intense nervousness or sensory overload. These actions can create a sense of control or provide temporary relief, albeit at the cost of physical harm.
Anxiety-related self-injury often requires strategies that target both the behaviour and the underlying anxiety. Techniques such as mindfulness, relaxation exercises, or therapeutic interventions can reduce stress and help individuals develop healthier ways to cope with their feelings. Creating a supportive environment where the person feels safe to express their concerns and emotions is also essential in addressing the anxiety that fuels self-injury.
Borderline Personality Disorder (BPD)
BPD has one of the strongest links with self-injury among mental health conditions. One reason is the intensity of emotions people with BPD can experience and the difficulty of bringing those emotions back down once they become overwhelming.
Research shows a strong connection between self-injury and difficulties with emotional regulation. For someone with BPD, feelings of rejection, abandonment, anger, shame or emotional pain can escalate quickly, while impulsivity can make it harder to pause and use another coping strategy. In that moment, self-injury may bring a temporary reduction in emotional tension — which can make the behaviour more likely to be repeated when similar distress returns.
PTSD
Post-traumatic stress disorder (PTSD) is another mental health condition closely associated with self-injurious behaviour. For individuals with PTSD, actions like head banging, sharp-object use, or self-biting may be an attempt to manage flashbacks, intrusive thoughts, or intense feelings of fear and helplessness. The physical pain of self-injury can momentarily distract from emotional pain or serve as an anchor in the present moment when dissociation occurs.
Interventions for PTSD-related self-injury focus on addressing the trauma at the root of the behaviour. Trauma-focused therapies, such as eye movement desensitisation and reprocessing (EMDR) or trauma-focused cognitive behavioural therapy (TF-CBT), can help individuals process their experiences and reduce distress.
Self-Injurious Behaviour in Mental Health Crisis Situations
Self-injury can happen alongside different mental health challenges. While every person’s experience is different, it can sometimes become a way of coping when what someone is feeling becomes too difficult to hold or express.
- Depression: When someone has been feeling low, empty or disconnected for a long time, self-injury may become a way of releasing emotional pain or simply feeling something again.
- Anxiety: Imagine living with constant worry and tension that keeps building. When it becomes overwhelming, self-injury may provide a temporary sense of release.
- Borderline Personality Disorder (BPD): Emotions can feel incredibly intense and change quickly. Rejection, conflict or the fear of losing an important relationship may trigger distress that feels impossible to manage in the moment.
- Post-Traumatic Stress Disorder (PTSD): A memory, sound, place or situation can suddenly bring difficult experiences back. For some people, self-injury becomes a way of coping when they feel overwhelmed or unsafe.
- Eating Disorders: Difficult feelings around food, body image, control, shame or self-worth can exist alongside self-injury, particularly during periods of increased emotional distress.
- Psychosis: Frightening or confusing experiences, including hearing or seeing things others do not, can cause significant distress. For some people, that distress may be accompanied by self-injurious behaviour.
Preventing SIB and Support
When someone is hurting themselves, we naturally want to make it stop. But sometimes the most useful thing we can do is look beyond that moment and try to understand what is making things so hard for them.
- Look at what happened before. Was the day particularly difficult? Did something change unexpectedly? Was there an argument, a demand or a situation they found hard to manage?
- Learn their early signs. Maybe they become quieter. Maybe they start pacing, withdrawing or becoming frustrated. Recognising these small changes can give us a chance to respond before everything becomes too much.
- Think about their surroundings. A busy room, constant noise, bright lights or too many people can be exhausting. Sometimes simply making the environment calmer can make a difference.
- Give them another way to tell you. Not everyone can say “I’m overwhelmed,” “I’m scared,” or “I need this to stop.” Communication might come through words, pictures, gestures or behaviour.
- Don’t overlook physical discomfort. If SIB appears suddenly or becomes more frequent, ask whether something could be hurting or making the person uncomfortable.
- Know what brings them back to calm. A familiar person, music, movement, quiet time, a favourite activity or simply having some space can all make difficult moments easier.
- Ask for support when things aren’t improving. Families and carers don’t have to work everything out alone. Mental health and behavioural professionals can help understand what is happening and find approaches that fit the person.
The aim is not simply “How do we stop SIB?” A better question is “What does this person need so they don’t have to reach this point?”
Therapies and Approaches That Reduce SIB
Reducing self-injurious behaviour often takes more than one intervention. Emotional distress, trauma, sensory overload and changes in mental health can overlap, which is why support needs to look at the whole person and what is happening around them.
- Positive Behaviour Support (PBS): Instead of focusing only on stopping SIB, PBS asks why the behaviour is happening. A functional assessment can explore what happens before and after SIB, possible triggers and what the person may be trying to communicate or manage. Support can then focus on reducing triggers and building safer ways to cope and communicate.
- Trauma-Informed Care: Past experiences can influence how someone responds to people, environments, demands or situations today. Trauma-informed support considers what may have happened to the person, what helps them feel safe and what could unintentionally increase their distress.
- PROACT-SCIPr-UK®: The focus begins with prevention. Teams learn to recognise early signs of distress, understand individual triggers and use proactive strategies and de-escalation before a situation reaches crisis point. Restrictive interventions are considered only when necessary to maintain safety, with an emphasis on the least restrictive response.
- Community Psychiatric Nursing (CPN): When SIB is connected with someone’s mental health, CPN support can explore changes in mood, anxiety, sleep, trauma, emotional regulation and overall mental wellbeing. Ongoing clinical input can also help identify changes early and adapt support as the person’s needs change.
These approaches have one important thing in common: SIB is not treated as a behaviour that simply needs to disappear. The focus is on understanding what is happening for the person and reducing the distress that may be driving it.
Mental Health Support and Crisis Intervention with Nurseline Community Services
At Nurseline Community Services, we are committed to providing compassionate, person-centred support for people experiencing mental health challenges, including those engaging in self-injurious behaviour. Through our Community Transition Services (CTS), we help people move seamlessly from hospital settings to supportive, home-like environments where they can regain stability and thrive. Our multidisciplinary team—including mental health professionals, occupational therapists, and behaviour specialists—works collaboratively to create tailored care plans that address both immediate needs and long-term goals. By integrating evidence-based practices, such as Positive Behaviour Support (PBS), we ensure that each person receives the right support to promote their safety and well-being.
In one recent case, a young person transitioning from acute care demonstrated significant improvement through our structured support. By identifying triggers for their self-injurious behaviour and implementing personalised interventions, including sensory tools and communication strategies, they were able to develop healthier coping mechanisms. This transformation highlights the importance of tailored approaches that empower people to lead fulfilling lives.
If you’re looking for comprehensive mental health support or crisis intervention for yourself, a loved one, or someone in your care, Nurseline Community Services is here to help. Contact us today to learn more about our services and how we can make a positive difference.
There is rarely one reason. SIB may appear during periods of intense emotional distress, anxiety or trauma, but it can also be linked to pain, sensory needs, communication difficulties or changes in the person’s environment. Understanding when it happens and what is happening around the person at the time can give important clues about why.
FAQs
Why Does Someone Develop Self-Injurious Behaviour?
There is rarely one reason. SIB may appear during periods of intense emotional distress, anxiety or trauma, but it can also be linked to pain, sensory needs, communication difficulties or changes in the person’s environment. Understanding when it happens and what is happening around the person at the time can give important clues about why.
Can Sensory Overload Trigger Self-Injurious Behaviour?
Yes. Noise, bright lights, crowds, touch or simply too much happening at once can become overwhelming. For someone who experiences sensory differences, SIB may appear when they have reached a point where they can no longer manage the level of stimulation around them.
What Should I Do When Someone Is Showing Self-Injurious Behaviour?
Focus on keeping the person safe without adding more pressure to an already difficult moment. Reduce noise and demands where possible, give them space if they need it and use the communication they are most comfortable with. Afterwards, think about what happened before the distress started and what seemed to help it settle. Repeated or increasing SIB should be discussed with an appropriate health or mental health professional.
Can Self-Injurious Behaviour Be Reduced or Prevented?
In many cases, yes. The starting point is finding out why it is happening for that person. This might mean addressing emotional distress or trauma, changing something in their environment, reducing sensory overload or finding a better way for them to communicate what they need. Approaches such as Positive Behaviour Support (PBS), trauma-informed care and specialist mental health support can help identify these patterns and develop support around the individual.